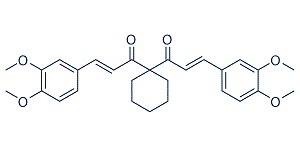
In the current study, we reveal a potential non-invasive therapeutic approach for enhancement of BBB permeability to facilitate CNS drug delivery, systemic pre-injection of VEGF. This result is consistent with an in vitro study showing that VEGF dose-dependently and reversibly enhanced permeability through cultured Sipeimine endothelial cell layers. In contrast, others have reported that systemic application of VEGF only increases the permeability of already compromised BBA. For example, VEGF increased the BBB permeability around the ischemic region of a mouse stroke model but not in the
contralateral hemisphere. However, our study demonstrates that VEGF can indeed enhance the permeability of the intact BBB in healthy mice in vivo. Moreover, this effect was observed at relatively low concentrations and was not associated with severe edema. These lower concentrations have also been shown to increase BBB permeability without induction of vascular proliferation, but continuous infusion led to retraction of astrocyte endfeet, monocyte infiltration, and neuroinflammation. We suggest that a single low dose of VEGF may transiently enhanced BBB permeability without disrupting neural homeostasis for safe CNS Forsythin delivery of neurotherapeutics. The absence of enhanced BBB permeability in some brain regions, which made MR images appear multifocal rather than homogeneous, may be due to the lag phase phenomenon, where local VEGF concentration fails to reach a threshold concentration due to its relatively brief plasma half-life. Previous studies also revealed that most VEGF receptors are located on the abluminal side of the BBB, which may limit access to systemic VEGF in some brain regions. While the identification of VEGF as an enhancer of BBB permeability represents the first step toward possible use for CNS drug delivery, much work remains to be done to elucidate the molecular mechanism. It was reported that VEGF can upregulate the mRNA expression of both VEGF and its receptors Flt-1 and Flk-1 in endothelial cells, possibly initiating a positive feedback cycle leading to enhanced BBB permeability. It is known that VEGF is a heparin-binding endothelial cell mitogen and angiogenic factor in vivo. Since angiogenesis depends on the migration of endothelial and peripheral cells, sprouting of new vessels might be linked to the reconstruction of existing vessels. Tissue reorganization requires activation of matrix metalloproteinases and VEGF enhances MMP-9 activity of in vivo ischemia models and in vitro BBB models. In addition, the endothelial nitric-oxide synthase pathway may also mediate transient opening of the BBB. It was reported that systemic administration of the selective eNOS inhibitor cavtratin in mice abrogated VEGF-induced BBB disruption and protected against neurologic deficits in the MS model system. Previous studies also highlighted a role for the src-suppressed C-kinase substrate in the regulation of BBB permeability. SSeCKS decreased VEGF expression by downregulating AP-1 and stimulating expression of angiopoietin-1. The contribution of these signaling mechanisms obviously depends on their sensitivity to serum VEGF concentration and duration of receptor interaction.
Author Archives: EpigeneticsCompoundLibrary
In agreement with this study we observed that elevated MAP1S levels were activity
TLR5 is expressed highly in some cancer cells, but is not expressed on mouse macrophages and conventional dendritic cells. TLR5 recognizes flagellin and initiates a signaling cascade through recruitment of MyD88 and activation of NF-kB. Recently, we and other groups determined that among TLR ligands, only the TLR5 ligand flagellin can induce TLR signaling in breast cancer cells. Triggering of TLR5 in cancer cells inhibits cancer cell proliferation and elicits strong antitumor activity. TLR5 signaling also exhibits radioprotective activity and improves the radiation efficacy of tumor cells in radiotherapy. However, TLR5 signaling in gastric cancer exhibits the opposite effect. The reason for these different outcomes of TLR5 signaling in different cancers is not clear. In this study, we focus on the role of MAP1S in TLR5-induced suppression of breast cancer. MAP1S is a recently identified adaptor protein of autophagic processes, which participates in microtubular coordination and regulates autophagy to suppress tumorigenesis. We observed that MAP1S levels were upregulated in response to flagellin Tubuloside-A treatment in human breast carcinomas
and MAP1S regulated cytokine expression induced by TLR5 signaling. Remarkably, MAP1S was associated with inhibition of cell proliferation and migration of flagellin-treated breast cancer cells. In addition, flagellin-induced elevation of MAP1S expression was involved in inhibitory feedback regulation of TLR5 signaling-induced late stage inflammation through the degradation of MyD88. Increasing evidence suggests that TLR5 signaling may play a role in tumorigenesis. Our previous results also Tenuifoliside-C showed that activation of TLR5 by flagellin elicited strong antitumor activity in breast cancer cells. In this study, we further investigated the underlying antitumor mechanisms of TLR5 signaling in breast cancer cells by examining the function of MAP1S. MAP1S is an important autophagic adaptor and is linked with suppression of tumorigenesis through the regulation of autophagy. We found that MAP1S levels are elevated in response to flagellin stimulation in MCF-7 cells, but it does not responded to LPS treatment. Flagellin-treated MCF-7 cells exhibited increases in the number of LC3 punctate foci, an autophagy marker. MCF-7 cells transfected with CD4/TLR4 or MAP1S alone showed few LC3 foci, while transfection of both plasmids induced larger numbers of foci, suggesting that MAP1S enhances TLR signalinginduced autophagy. Furthermore, knockdown of MAP1S dramatically decreased expression of the cytokines IL-8 and TNF-a and decreased NF-kB activity induced by TLR5 signaling. Taken together, these observations indicate that MAP1S is an autophagic regulator involved in TLR5 signaling in breast cancer cells. Consistent with our previous reported results, we demonstrated that flagellin suppressed proliferation of breast cancer cells. Furthermore, the whole-cell MALDI-TOF MS assay showed that flagellin inhibited MCF-7 cell state of activation globally. We also found MAP1S played a critical role in tumor suppression induced by flagellin treatment. Knockdown of MAP1S almost completely abrogated the inhibition of tumor growth and migration by flagellin treatment, which is consistent with a previous report showing that MAP1S deficient mice frequently develop tumors. We observed G1/S arrest, a significant decrease of cell cyclin protein CyclinD1 and increased p27 levels in MCF-7/shCtrl cells upon flagellin treatment, while there were no obvious changes in CyclinD1 and p27 levels in flagellin-treated MCF-7/shMAP1S cells. These results indicated MAP1S played an important role in antitumor activity of flagellin/ TLR5 signaling in MCF-7 cells. MAP1S enhances autophagic activity and is induced by stress exposure, indicating autophagic activation.
The extracellular concentration of adenosine can be increased as a result of neural activity
Allowing adenosine to mediate state-dependent actions that depend on prior activity in the nervous system. Some of this adenosine arises from prior release of ATP from astrocytes. However there is evidence for direct adenosine release from neurons. In the cerebellum this arises from exocytosis, but in other brain regions, such as hippocampus and cortex, direct activitydependent release of adenosine appears to be mediated via facilitative transporters. The link between neural activity and the production of intracellular adenosine which can be transported into the Anemarsaponin-BIII extracellular space remains unclear. There has been a general idea that the metabolic load of neuronal signalling causes consumption of ATP with consequent production of intracellular adenosine; this would then be extruded from the cell by adenosine clearance mechanisms such as facilitative transporters. Together, these two systems would represent activity-dependent release of adenosine into the extracellular environment. Infusion of adenosine into a single hippocampal pyramidal cell will cause depression of the synaptic inputs to that cell via activation of A1 receptors, suggesting that elevated levels of intracellular adenosine will readily be transported into the extracellular space. On this basis, any process that increases endogenous adenosine levels in neurons should therefore also affect its extracellular concentration. Metabolic processes that consume ATP will cause an increase in intracellular adenosine. As a very large proportion of the brain’s energy
budget is consumed by neurons pumping out the Na + that has entered during signalling, the activation of the ATPases is an attractive candidate mechanism to underlie a significant degree of activity-dependent adenosine efflux. The adenosine concentrations observed in this study are slightly higher than the Salvianolic-acid-B reported EC50s of the adenosine A1 receptor of around 1 mM, measured with respect to presynaptic inhibition of neurotransmission, in IP patients we observed no discrepancy between verbal and performance IQ scores. In fact, our participants showed a homogeneous profile. Our sample was not wide, but it showed the same distribution percentage of neurological manifestations reported in the literature. We found that 2 patients out of 10 were affected by mental delays resulting from neurological signs and 1 patient out of 10 was affected by mental delay without any neurological signs. This latter observation is particularly interesting because it suggested that patients with IP might be affected by mental delay also when no neurological damage was present and allowed us to separate mental delay from the neurological framework. The remaining patients with IP manifested no mental retardation, but a detailed cognitive assessment allowed us to detect the presence of learning disabilities. In particular, the learning abilities most affected were arithmetic reasoning and reading skills. In the psychological literature, a comorbidity between dyslexia and dyscalculia is often reported; it is often associated with two largely independent cognitive deficits, namely, a phonological deficit in the case of dyslexia and a deficit in the number module in the case of dyscalculia. In a review study, Jordan reported that reading difficulties aggravated rather than caused mathematical difficulties because compensatory mechanisms associated with reading are less available when dyslexia and dyscalculia co-occur. Furthermore, in our sample reading and arithmetic difficulties cooccurred in 4 patients out of 6. Reading seemed more affected in terms of accuracy than speed and comprehension, whereas all aspects of arithmetic were compromised.
The heterogeneity in the cognitive phenotype observed in our patient cohort
It is also possible that the heterogeneity of the cognitive phenotype is due to the IKBKG/NEMO mutation, which produces different phenotypic outcomes in mental functioning as well as physical characteristics. Specifically, our results suggest that the learning abilities most affected are arithmetic reasoning and reading skills, which are reported here for the first time as specific deficits in IP. Therefore, when IP is diagnosed, patients should always be submitted to a cognitive assessment specifically focused on learning skills and should be included in preventive educational programs. The IP syndrome is very problematic because neither the type of IKBKG/ NEMO genetic mutation nor the NEMO/IKKgamma protein affected domain is correlated with the severity of the IP phenotype. Although the presence of learning disabilities also in IP patients without any mental retardation is a significant finding, the pathophysiology of this defect must still be addressed. One challenging approach would be to perform functional MRI studies of the brain to identify any impaired cerebral functions underlying learning deficits in this population. In conclusion, the present study enrols learning disability amongst the CNS defects associated to IP disorder and supports a role of the IKBKG/NEMO gene as a genetic determinant of such a defect. A consequence of the IKBKG/NEMO mutation that might produce different phenotypic outcomes also in mental functioning. Accordingly, we would like to underline the importance of early assessment of learning abilities in individuals with IP who have no mental retardation to prevent the onset of deficits. A very recent study by GinieriCoccossis et al. investigated the quality of life of Ganoderic-acid-F children affected by specific learning disabilities and found that they had poorer emotional well-being, lower self-esteem and a higher level of dissatisfaction in their relationships with family and friends than children without these deficits. In line with this result, Michopoulou et al. also observed psychological problems, such as anxiety, depression, anger and disruptive behaviour, in these children. To avoid stigmatizing effects due to ongoing difficulty in school performance, it is important to submit children with IP to precocious, targeted treatment. Compared with mental delay or other mental disabilities, learning disabilities do not seem to cause any major psychosocial impairment. Nevertheless, failure to achieve academically can become a source of distress or external pressure for children and parents. If these difficulties are not treated at an early age, they can become long-standing and affect psychological development as well as the possibility of achieving professional fulfilment. Therefore, we would like to highlight the urgency of making an early diagnosis of learning disability in girls with IP by means of a comprehensive and thorough neuropsychological assessment, performed by a qualified clinician with regular follow-ups. Finally, we also suggest that re-educational training should be aimed
towards developing appropriate skills and coping mechanisms. Human study showed that blood pressure decrease in the eNOS 894TT carriers was greater than the other genotypes carriers after the exercise training. Therefore, subjects carrying the eNOS 894TT genotype may have low NO in vivo and are more susceptible to endothelial dysfunction, which might increase the risk of MI. The present meta-analysis results of homozygous and recessive genetic models can Benzoylpaeoniflorin account for the above hypothesis. Nevertheless, the number of TT genotype is relatively small in Asia populations and the 95%CI line of the pooled OR for Asia populations is longer than that for non-Asia population studies in Figure 1 and 2.
The ocular surface can be affected can be examined clinically using a topical application of sodium fluorescein
Previous meta-analyses of studies investigated the prognostic value of molecular markers in different malignancies. These include VEGF and p53. To date, no such Saikosaponin-C meta-analysis evaluated ENT1 in pancreatic cancer treated with gemcitabine. Furthermore, low hENT1 has been associated with poor prognosis in pancreatic cancer managed with gemcitabine-based chemotherapy. Other studies have not shown any significant link between hENT1 and PCGC survival. However, the number of patients included in each study was small. Therefore, it was essential to combine and analyze the data to obtain acceptable results. In the present meta-analysis, we enrolled 12 studies related to the effects of low hENT1 expression on PCGC survival. In all these studies, hENT1 expression was detected by immunohistochemistry or PCR with surgical specimens. Meta-analysis suggested that low hENT1 was a factor associated with poor prognosis in PCGC. We further conducted subgroup analysis, in which hENT1 expression was measured by IHC. The results showed that low expression of hENT1 was closely associated with poor prognosis in patients with PCGC. Furthermore, hENT1 expression by PCR also showed significant impact on patients’ OS. The recent PRODIGE 4/Accord 11 trial results have expanded the therapeutic options in metastatic PAC, by demonstrating the superiority of FOLFIRINOX regimen in comparison with gemcitabine alone. This study included only patients who were aged below 76 years, with a good performance status, no cardiac ischemia, and normal or nearly normal bilirubin levels. However, no study investigated whether this regimen or other regimens were indicated for patients with low hENT1 expression in an adjuvant setting. Several studies reported methods involving histopathologic or cytopathologic diagnosis, including US- and CT-guided percutaneous biopsy, transpapillary pancreatic duct biopsy, and cytologic evaluation of pancreatic juice obtained via ERCP. The ability to visualize small lesions with EUS is excellent, and, unlike other methods, the entire pancreas is readily imaged. Thus, EUS-FNA is widely used as a cytological and histological sample collection tool in pancreatic cancer. Evaluation of hENT1 in pancreatic cancer tissue acquired with minimally invasive procedures warrants further study to determine the potential to individualize gemcitabine therapy in the majority of pancreatic cancer patients who present with locally advanced or metastatic disease. Meta-analysis of prognostic literature is associated with a number of inherent limitations. Retrospective study design is one of the key limitations. Only three of the studies included in the current meta-analysis involve a prospective design. The availability and adequacy of corresponding clinicopathological data is also a significant consideration in retrospective studies of this type. We identified several studies reporting incomplete histopathological datasets. Other disadvantages include the following: First, we failed to review unpublished articles and abstracts, as most of the data were not required. Second, we included
eligible English and Chinese studies only, suggesting a Gentiopicrin language bias. Third, HR calculation from data or extrapolation from survival curves in the articles, in the absence of directly reported HR values, introduced an element of decreased reliability. Our meta-analysis also displayed significant strengths. First, the quality of studies included in the meta-analysis was satisfactory and strictly met the inclusion criteria. Second, the summary risk estimates of our study did not show any evidence of heterogeneity and publication bias. Third, we performed subgroup analysis by measuring hENT1.